



Finding a pale or white patch on your child’s skin can be worrying, particularly if you are unsure why it has appeared or whether it will spread. Vitiligo is one possible cause and can begin during childhood or adolescence.
Vitiligo causes areas of skin to lose their natural pigment, but it is not contagious and is not caused by poor hygiene, diet or anything you have done. Treatment may help restore some colour, control active disease and support your child’s confidence and wellbeing.
What Is Childhood Vitiligo?
Vitiligo develops when pigment-producing cells called melanocytes stop working or are destroyed, causing lighter or white patches on your child’s skin. The patches can affect one small area or several parts of the body.
Some children develop new patches gradually, while others experience periods of activity followed by long periods of stability. Vitiligo can affect children of every skin tone, although the contrast may be more noticeable on darker skin.
Why Does Vitiligo Develop?
There is no single known cause of vitiligo. Non-segmental vitiligo is generally considered an autoimmune condition in which your child’s immune system mistakenly targets melanocytes.
Genetics, immune-system changes and environmental factors may all contribute to the condition developing. A family history can increase susceptibility, but many children with vitiligo have no known affected relatives.
Vitiligo Is Not Your Child’s Fault
You may wonder whether illness, food, stress or something else triggered your child’s vitiligo. It is important to know that the condition is not caused by anything you or your child did.
There is no reliable evidence that ordinary foods, poor hygiene or normal childhood activities cause vitiligo. You can help your child by focusing on appropriate medical care, sun protection and reassuring them that they are not responsible for the changes in their skin.
What Can Vitiligo Look Like in Children?
You may notice flat areas of your child’s skin that are lighter than the surrounding skin and may gradually become completely white. The patches usually have clearly defined borders and typically remain smooth rather than becoming rough or scaly.
Common areas include the face, hands, fingers, elbows, knees, feet and skin around the eyes or mouth. Hair growing within an affected patch can sometimes turn white, including scalp hair, eyebrows or eyelashes.
What Early Signs Might You Notice?
You may first notice a small pale patch that becomes more obvious during summer when the surrounding skin tans. Early changes can appear around your child’s fingertips, eyelids, mouth or areas exposed to frequent rubbing.
Vitiligo usually does not cause pain, although mild itching can occur in some children. Taking occasional photographs in similar lighting can help you monitor changes without checking your child’s skin excessively.
Clinical Tip
Take photographs of your child’s skin from the same angle and in similar lighting every few months. This can make it easier for you and their dermatologist to see whether patches are changing.
Daily checking is usually unnecessary and can make normal lighting differences look like progression. Your dermatologist may also use standardised photographs during follow-up appointments.
Evidence Note
Systematic reviews suggest that childhood vitiligo can affect confidence, social experiences, emotional wellbeing and overall quality of life. The impact can vary considerably between children.
How your child feels may depend on their age, where the patches appear, how visible they are and the reactions of other people. This is why emotional wellbeing should be considered alongside the physical appearance of the skin.
How Can Non-Segmental Vitiligo Affect Your Child?

Non-segmental vitiligo is the most common form and often affects both sides of your child’s body. You may notice patches around both eyes, on both knees, across several fingers or in other areas, although the pattern is not always perfectly symmetrical.
New patches can sometimes appear after a period of stability, and this form can be associated with other autoimmune conditions such as thyroid disease. Your healthcare professional may therefore ask about your child’s general health and family medical history.
What Is Segmental Vitiligo?
Segmental vitiligo usually affects one side or one localised area of your child’s body and often begins at a younger age. You may notice patches on the face, trunk or one limb.
The condition often spreads for a limited period before becoming stable. If hair within the affected area turns white, repigmentation may be more difficult because hair follicles can play an important role in restoring pigment.
Why Can Skin Injuries Trigger New Patches?
You may notice new vitiligo patches appearing where your child has experienced a cut, graze, burn or repeated friction. This response is known as the Koebner phenomenon.
Your child can still play, exercise and take part in normal activities. You can reduce unnecessary irritation by preventing sunburn, treating itchy skin promptly and ensuring clothing or sports equipment does not repeatedly rub the same areas.
What’s the Difference Between Segmental and Non-Segmental Vitiligo?
Understanding the type of vitiligo your child has can help explain how the condition may behave. It can also help their dermatologist choose the most suitable approach to treatment and monitoring.
The two main patterns differ in distribution, progression and association with other conditions. Your child’s individual experience may still vary from these general patterns.
| Feature | Non-Segmental Vitiligo | Segmental Vitiligo |
| How common is it? | Most common type in children | Less common |
| Pattern | Often affects both sides of the body | Usually affects one side or localised area |
| Progression | May alternate between activity and stability | Often spreads for a limited period before stabilising |
| Associated conditions | More often linked with autoimmune conditions | Less commonly associated with autoimmune disease |
| White hairs | Can occur | More commonly seen within affected patches |
| Treatment | Aims to control progression and encourage repigmentation | Depends on location, stability and extent |
What Other Conditions Can Look Like Vitiligo?
Not every pale patch on your child’s skin is caused by vitiligo. Conditions such as pityriasis alba, pityriasis versicolor, eczema-related pigment change, scars and other skin conditions can create lighter areas.
A dermatologist can look at the colour, texture and pattern of your child’s patches to help identify the cause. You should arrange an assessment if the patches are spreading, changing or associated with scaling, discomfort or altered skin texture.
How Is Childhood Vitiligo Diagnosed?
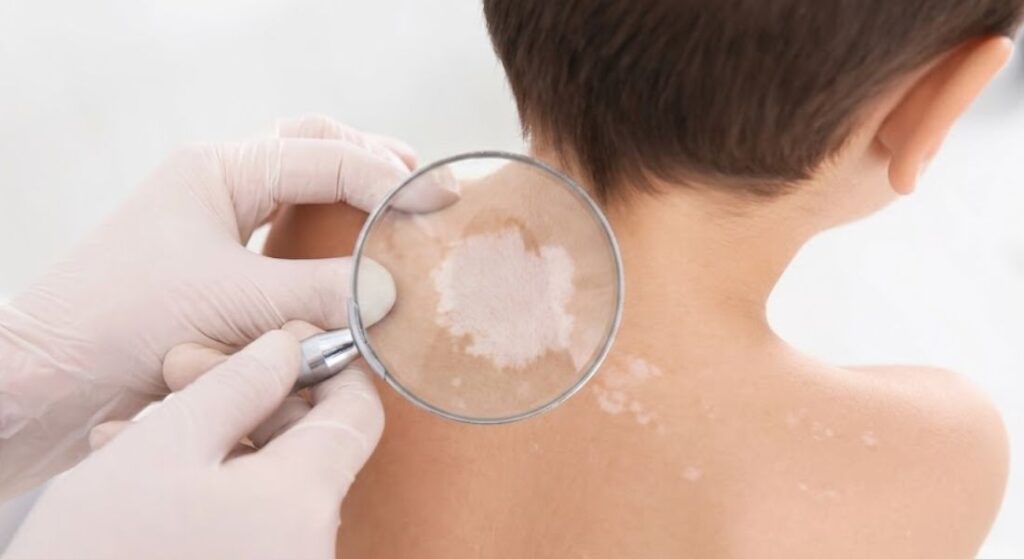
Vitiligo is usually diagnosed by examining your child’s skin and reviewing their medical history. The clinician will consider the colour, borders, distribution and texture of the patches and ask how they have changed.
A Wood’s lamp may be used to make pigment loss easier to see and help distinguish vitiligo from other causes of lighter skin. A skin biopsy is rarely required unless the diagnosis remains uncertain.
Might Your Child Need Blood Tests?
Children with non-segmental vitiligo have an increased likelihood of some autoimmune conditions, particularly thyroid disease. This does not mean your child will necessarily develop another autoimmune condition.
British Association of Dermatologists guidance recommends thyroid-function and antithyroid-antibody screening for people with vitiligo, including children when appropriate for their age. Your child’s healthcare professional will decide which tests are appropriate based on symptoms, medical history and family history.
Is Your Child’s Vitiligo Active or Stable?
Active vitiligo means that new patches are appearing or existing areas are becoming larger. Stable vitiligo means your child has had no significant new patches or progression for a period of time.
Photographs and follow-up examinations can help the dermatologist understand whether the condition is changing. Knowing whether your child’s vitiligo is active or stable can influence which treatments are most appropriate.
How Can Vitiligo Affect Your Child Emotionally?
Vitiligo usually does not make your child physically unwell, but visible skin changes can affect confidence and emotional wellbeing. You may notice self-consciousness, worry about questions from other people or reluctance to take part in certain activities.
The emotional impact is not always related to how much skin is affected. Even a small visible patch can be important to your child, so it helps to ask how they feel rather than assuming they are coping well.
Research Insight
Research into childhood vitiligo shows that quality-of-life effects can involve confidence, friendships, school experiences and emotional wellbeing. These concerns may be important even when only a small area of skin is affected.
Your child’s healthcare team should therefore consider how vitiligo affects everyday life as well as looking at the skin itself. Emotional support can be an important part of successful long-term care.
How Can You Support Your Child at Home and School?
You can support your child by asking how they feel about their skin and giving them space to talk openly. Their feelings may change as they grow, begin school, meet new people or notice changes in their vitiligo.
Simple reassurance that vitiligo is not contagious and does not make your child unhealthy can help build confidence. If they become withdrawn, anxious or experience teasing, you may also want to involve teachers or seek additional emotional support.
How Should You Protect Your Child’s Skin From the Sun?

Vitiligo patches contain little or no melanin, so your child’s affected skin can burn more easily. Use a broad-spectrum SPF 50 or higher sunscreen with good UVA protection on exposed areas.
Reapply sunscreen regularly, particularly after swimming, towel-drying or heavy sweating, and use clothing, hats and shade for additional protection. You can also ask your child’s GP or dermatologist whether vitamin D advice or an age-appropriate supplement is needed.
Does Every Child With Vitiligo Need Treatment?
Not every child needs treatment aimed at restoring pigment. You may prefer monitoring, sun protection and emotional support if your child has limited stable patches and feels comfortable with their appearance.
Treatment may be considered when vitiligo is active, spreading or affecting your child’s confidence and quality of life. Their clinician will consider age, skin tone, disease pattern and how practical the treatment routine will be for your family.
How Can Topical Corticosteroids Help?
Topical corticosteroids can be used for selected small areas of active vitiligo by reducing immune activity in your child’s skin. The strength and duration of treatment depend on age and the area being treated.
More delicate areas such as the face, eyelids and skin folds may require different treatments because they are more vulnerable to steroid side effects. You should follow the prescribed amount and schedule carefully to reduce the risk of skin thinning.
Could Tacrolimus or Pimecrolimus Be Suitable?
Tacrolimus ointment and pimecrolimus cream reduce immune activity without causing the skin thinning associated with topical steroids. They can therefore be useful on delicate areas such as your child’s face, eyelids, neck or skin folds.
Your child may initially notice mild warmth, stinging or burning when treatment is applied. Repigmentation can develop gradually, although areas such as the fingers, toes or patches containing white hair may respond less completely.
When Might Your Child Need Narrowband UVB Phototherapy?
Narrowband UVB phototherapy may be considered when your child’s vitiligo is widespread, actively spreading or significantly affecting quality of life. Treatment uses carefully controlled ultraviolet B light under specialist dermatology supervision.
Appointments are often required two or three times each week for several months, so the practical commitment should be discussed before treatment begins. Repigmentation often responds better on the face and trunk than on the hands and feet, although results vary.
Ruxolitinib Cream: What Should You Know?
Ruxolitinib cream is a topical Janus kinase inhibitor that targets immune signalling involved in non-segmental vitiligo. It is licensed for people aged 12 years and over with non-segmental vitiligo involving the face.
Your dermatologist may consider it when your child is eligible and first-line topical treatments have not worked or are unsuitable. Treatment requires specialist supervision and may need to continue for several months before meaningful repigmentation becomes visible.
UK Guidance Note
NICE recommends ruxolitinib cream as an option for people aged 12 years and over with non-segmental vitiligo involving the face when first-line topical treatments have not worked or cannot be used. It should be started and supervised by an appropriately experienced clinician.
Its safety and effectiveness have not been established for children under 12. Your dermatologist can explain whether your child meets the treatment criteria and what monitoring may be needed.
What Other Vitiligo Treatments Are Being Studied?
Researchers are continuing to investigate treatments that target the immune processes involved in vitiligo more precisely. Your dermatologist may also discuss targeted light treatment for selected small or localised patches.
Surgical techniques that transfer pigment-producing cells are generally reserved for carefully selected stable disease and are not routinely used in children. Many newer approaches still require stronger evidence about their long-term safety and effectiveness.
Myth vs Fact
| Myth | Fact |
| Vitiligo is contagious | It cannot be passed from one person to another |
| Poor hygiene or diet causes vitiligo | Ordinary foods and hygiene do not cause the condition |
| Sun exposure is harmless | Vitiligo patches can burn more easily and need protection |
| Vitiligo always spreads | Some children have stable patches for long periods |
| Every child needs treatment | Some children may only need monitoring and support |
| Treatment guarantees normal pigment | Repigmentation varies and may not be complete or permanent |
| Vitiligo only affects appearance | It can also affect confidence and emotional wellbeing |
Key Takeaways
- Vitiligo causes smooth pale or white patches and is not contagious.
- It is not caused by poor hygiene, ordinary foods or anything your child has done.
- A dermatologist can distinguish vitiligo from other causes of pale skin.
- Non-segmental and segmental vitiligo can behave differently.
- Age-appropriate thyroid screening may be recommended.
- Treatment can include topical medicines or narrowband UVB phototherapy.
- Ruxolitinib cream may be an option for eligible young people aged 12 and over.
- Sun protection is an important part of everyday care.
- Emotional wellbeing should be considered alongside skin treatment.
- No treatment can guarantee complete or permanent repigmentation.
Frequently Asked Questions
1. What causes vitiligo in children?
Non-segmental vitiligo is generally considered an autoimmune condition in which your child’s immune system targets pigment-producing melanocytes. Genetics, immune changes and environmental factors may contribute, but it is not caused by poor hygiene, ordinary foods or anything you have done.
2. Is childhood vitiligo contagious?
No. Your child cannot pass vitiligo to another person through touching, hugging, swimming, sharing towels or attending school because the condition is not caused by an infection.
3. Can vitiligo spread over time?
Yes, some children develop new patches over time, while others have one or two areas that remain stable for years. Your child may experience periods of activity followed by long periods when the condition does not noticeably change.
4. How is childhood vitiligo diagnosed?
Your child’s dermatologist will usually diagnose vitiligo by examining the skin and reviewing their medical and family history. A Wood’s lamp may help show pigment loss more clearly, while blood tests may be used to investigate associated autoimmune conditions rather than confirm vitiligo itself.
5. Can vitiligo be cured?
There is currently no guaranteed cure for vitiligo. Treatment may help your child regain some pigment, control active disease or reduce contrast between affected and unaffected skin, but results vary.
6. What treatments are available for childhood vitiligo?
Your child’s treatment may include topical corticosteroids, tacrolimus, pimecrolimus or narrowband UVB phototherapy. Eligible young people aged 12 years and over with non-segmental facial vitiligo may also be considered for ruxolitinib cream.
7. Does vitiligo affect your child’s overall health?
Vitiligo itself usually does not make your child physically unwell, but it can be associated with certain autoimmune conditions, particularly thyroid disease. Your child’s healthcare professional can advise whether thyroid screening or other investigations are appropriate.
8. Can sunlight make vitiligo worse?
Vitiligo patches have little or no melanin and can therefore burn more easily. You can protect your child’s skin with high-factor sunscreen, suitable clothing and shade while avoiding sunburn.
9. How can you support your child emotionally?
You can help by listening to your child’s concerns and reassuring them that vitiligo is not their fault or something they can pass to others. Addressing teasing early and involving teachers when appropriate can also protect confidence and emotional wellbeing.
10. What is the outlook for children with vitiligo?
The course varies from one child to another, with some patches remaining stable and others changing over time. Treatment and follow-up may help your child manage active disease, encourage repigmentation and maintain a good quality of life.
Final Thoughts: Helping Your Child Live Well With Vitiligo
Childhood vitiligo can be a long-term condition, but appropriate treatment, sun protection and emotional support can help your child manage it well. Early assessment can also establish the diagnosis and identify whether the condition is active.
An assessment with an experienced paediatric dermatologist in London can help your child understand their treatment options and receive an individual care plan. Ongoing support can also protect their skin health, confidence and quality of life.
References:
- Tissera, K.A., Hawryluk, E.B. and Garza-Mayers, A.C. (2025) ‘A retrospective comparison of narrowband-UVB phototherapy in pediatric versus adult vitiligo’, Children, 12(4), article 466. Available at: https://www.mdpi.com/2227-9067/12/4/466
- Pala, V., Ribero, S., Quaglino, P. and Mastorino, L. (2023) ‘Updates on potential therapeutic approaches for vitiligo: Janus kinase inhibitors and biologics’, Journal of Clinical Medicine, 12(23), article 7486. Available at: https://www.mdpi.com/2077-0383/12/23/7486
- Gianfaldoni, S. et al. (2018) ‘Vitiligo in children: A review of conventional treatments’, Open Access Macedonian Journal of Medical Sciences. Available at: https://pmc.ncbi.nlm.nih.gov/articles/PMC5816302/
- Kanwar, A.J. and Kumaran, M.S. (2012) ‘Childhood vitiligo: Treatment paradigms’, Indian Journal of Dermatology. Available at: https://pmc.ncbi.nlm.nih.gov/articles/PMC3519254/
- Nathalie, J. et al. (2021) ‘Health-related quality of life in paediatric patients with vitiligo: A systematic review and meta-analysis’, Journal of the European Academy of Dermatology and Venereology. Available at: https://pubmed.ncbi.nlm.nih.gov/34013610/
- Tarafdar, N. and Varambally, M. (2026) ‘Psychiatric comorbidities and quality-of-life burden in pediatric patients with vitiligo: A systematic review and meta-analysis’, Pediatric Dermatology. Available at: https://pubmed.ncbi.nlm.nih.gov/41084130/
- Eleftheriadou, V., Atkar, R., Batchelor, J. et al. (2022) ‘British Association of Dermatologists guidelines for the management of people with vitiligo 2021’, British Journal of Dermatology, 186(1), pp. 18–29. Available at: https://onlinelibrary.wiley.com/doi/10.1111/bjd.20596